A practical guide consisting of information on the pricing of EHR and EMR systems, the costs involved in implementing them, maintenance expenses, and long-term budgeting for medical practices in the United States.
The subscription price is given in an EHR quote. At the same time, a useful EHR budget shows you the amount needed to run your practice, including clinical documentation, scheduling, billing, connected systems, trained staff, and reliable continuous support. The ModuleMD guide combines these costs so you can compare packages and plan your investment with confidence.
Explore ModuleMD plans and pricing to find the right fit for your practice.
How much does EHR software cost in 2026?
There is no single price that fits every practice. Software Advice’s 2026 EMR pricing guide reports an average buyer budget of $382 per provider per month, based on more than 15,000 advisor interactions from August 2023 through August 2025. This is a historical buyer-budget benchmark published in 2026, not a verified average transaction price or an all-inclusive implementation cost.
For your practice, calculate the quoted subscription plus required modules and usage charges, then add migration, implementation, training, and transition expenses. The most useful comparison shows monthly operating payments, first-year cash spending, and three-year total cost of ownership.
| Budget view | What it answers |
|---|---|
| Monthly recurring cost | What will we pay to keep the agreed package running? |
| First-year cash budget | What funds do we need for launch and the first 12 months? |
| Three-year ownership cost | What will subscriptions, renewals, initial work, and internal effort cost over time? |
For example, three providers at an assumed $400 monthly rate, $150 in monthly additions, and $6,000 in implementation payments produce a $22,200 first-year cash budget. This is an illustrative calculation, not a ModuleMD price quote. The calculator below lets you replace every assumption.
Reviewed October 12, 2026. All figures are in US dollars. Scope: US outpatient software purchasing, rather than hospital enterprise deployments or custom software development.
What 2026 EHR Market Research Actually Tells Us
Market research can help you frame a budget, but a buyer’s spending expectation, a modeled estimate, and a contracted price measure different things. Read the method before putting a number into your business plan.
Software Path’s 2026 EHR project research analyzes 17,674 selection projects recorded from January 2020 through July 2026, with a predominantly US outpatient sample. Its modeled annual budget per practice is $8,701 for 2026. The model holds benchmark rates constant and applies them to the changing buyer mix; it does not measure actual 2026 invoices or prove that EHR prices have fallen.
| Evidence type | Useful for | Do not treat it as |
|---|---|---|
| Buyer budget research | Understanding reported spending expectations | A guaranteed available price |
| Modeled market budget | Understanding how buyer composition affects expected spending | An observed change in vendor prices |
| Written practice-specific quote | Planning the proposed scope and contract | A complete budget until exclusions are resolved |
| Illustrative calculator scenario | Testing provider counts, fees, and renewal assumptions | A researched market average |
Why deployment and scope still matter
The same research reports that 93.32% of selection projects in the first seven months of 2026 preferred cloud deployment. Even so, a cloud proposal still demands a close look at hosting terms, ongoing support, interface integration, and day-to-day local IT responsibilities.
EHR software cost versus EMR software cost
Whether your search starts with EHR system cost or EMR system cost, compare the work the system must support. The product label alone does not establish affordability. Map documentation, prescribing, scheduling, billing, patient communication, reporting, and specialty requirements before comparing fees.
What is the average cost of an EHR system?
The sources reviewed here do not establish a representative, all-inclusive 2026 US market average. Use the research as context, then calculate your own cost using the correct billing unit, package, practice size, and implementation scope.
Step 1: Understand EHR Pricing Models and Packages
Start with two questions: how is the fee calculated, and what does the package include? A per-provider quote and a per-user quote may cover very different numbers of paid accounts. A lower tier may also leave out a workflow your practice requires.
| Model | Calculation | Question to ask |
|---|---|---|
| Per provider | Licensed providers × provider rate | Do physician, advanced practice, and part-time rates differ? |
| Per user | Paid accounts × user rate | Are front desk, billing, and signing staff charged separately? |
| Per practice or location | Base fee plus applicable locations | What provider, account, and location limits apply? |
| Tiered package | Package fee plus required additions | Which tier supports the complete workflow? |
| Usage based | Expected units × unit price | What allowances, minimums, and overages apply? |
| License plus maintenance | License, hosting, support, and upgrades | Who pays for infrastructure and future upgrades? |
| Outsourced billing service | Contracted fee, sometimes tied to collections | What collections are counted and what labor is included? |
Cloud versus locally hosted EHR costs
For a cloud system, confirm whether hosting, backups, updates, support, and service availability commitments are included. Budget for devices, connectivity, and local IT needs where applicable. A subscription does not eliminate every infrastructure expense.
For a locally hosted system, price servers, backups, maintenance, IT labor, and upgrades alongside the license. Compare both deployment options over the same period and scope. A cloud system is not always cheaper, and a one-time license does not mean there are no ongoing costs.
What to check before buying EHR or EMR software
Ask for a sample invoice using your expected provider mix, locations, and monthly activity. Request a written list of included, optional, and usage-based items. Check renewal increases, provider minimums, cancellation terms, and data export before signing.
When a quote says a feature is available, ask whether it is included in your proposed package or requires another subscription, project, or third-party agreement.
Build the scope around your electronic health records requirements and practice management workflows. Then ask which plan delivers the complete clinical and administrative process.
Step 2: Build Your EHR Implementation Budget
Implementation prepares your records, people, equipment, and workflows for daily use. A useful quote describes deliverables and responsibilities for each activity.
HealthIT.gov’s health IT implementation guidance, updated in April 2026, addresses configuration, validation, maintenance, and system interfaces. For budgeting, identify who will perform this work and whether the proposal includes it. The guidance supports implementation planning; it does not set software prices.
| Cost component | Budget scope | What to confirm |
|---|---|---|
| Configuration | Users, roles, locations, templates, workflows | Included setup versus custom work |
| Data migration | Extraction, mapping, import, validation | Structured data, attachments, history, exceptions |
| Interfaces | Lab, device, hospital, and other connections | Exact systems, setup fees, recurring fees |
| Training | Provider, front desk, billing, administrator | Included hours, format, additional sessions |
| Launch support | Remote or onsite assistance | Travel, coverage hours, extended support |
| Devices and IT | Computers, tablets, microphones, network | Reusable equipment and required upgrades |
| Transition overlap | Legacy access and parallel subscriptions | Overlap period and archive arrangements |
| Internal work | Training, meetings, testing, validation | Staff hours and realistic labor assumptions |
Data migration is a scope decision
A searchable document archive and structured clinical data are different outcomes. Ask which fields, attachments, medication histories, results, and financial records will transfer. Agree on validation responsibilities and how failed or incomplete imports will be resolved.
Recurring expenses to review
Check prescribing services, clearinghouse transactions, eligibility checks, reminders, patient statements, fax, payment processing, storage, device interfaces, AI usage, additional training, and support levels. These items may be included, optional, or separately charged. Record the contract terms instead of assuming every item is an extra fee.
Switching EHR systems
A replacement project can also involve old-system termination fees, data extraction, archival access, and subscription overlap. Keep medication and supply purchases outside the software budget. Track cash expenses separately from the value of staff time so your practice can plan both cash flow and workload.
How Much Does EHR Maintenance Cost?
EHR maintenance is the ongoing work needed to keep the agreed system usable and supported after launch. Its cost depends on what the subscription or maintenance agreement already covers and what your practice must arrange separately.
| Maintenance area | Budget check |
|---|---|
| Software updates and support | Are routine updates and the required support level included? |
| Interfaces and connected systems | Are monitoring, changes, and repairs covered by recurring fees? |
| Local equipment and connectivity | Who maintains devices, networks, and backups within the practice’s responsibility? |
| Ongoing staff training | What will onboarding new staff or retraining existing staff cost? |
| Locally hosted infrastructure | Who pays for server support, storage, upgrades, and recovery work? |
| Renewal and service changes | Which fees can rise, and when can the practice change its plan? |
Avoid counting maintenance twice
If hosting, routine updates, and standard support are included in a cloud subscription, do not add an invented maintenance percentage on top. Budget only the separately chargeable services and your own operational responsibilities. For a locally hosted system, obtain an explicit maintenance and infrastructure schedule.
An illustrative maintenance allowance
Suppose separately contracted IT support costs $200 a month and additional annual training costs $600. Those items add $3,000 a year: $200 × 12 + $600. This example is a budgeting calculation, not a market maintenance rate, and it excludes any maintenance already included in the software fee.
Keep a reserve for known equipment replacements or interface changes based on your own inventory and plans. Record the assumption and owner for each item instead of applying an unexplained percentage to the whole EHR contract.
Step 3: Estimate EHR Cost by Practice Size
The table below shows annual subscription scenarios using assumed monthly rates. It is a planning model, not a market survey, a ModuleMD quote, or a complete implementation budget.
EHR budget calculator
Sample inputs demonstrate the method. Replace them with written quotes. Results are estimates, not ModuleMD pricing.
The annual increase applies to all recurring charges in years two and three. Provider count and usage stay unchanged. One-time cash payments occur in year one; internal labor value is added once to economic cost. Taxes and financing are excluded. A blended provider rate may conceal different contract rules; use a detailed worksheet for complex groups.
| Providers | At $250 per month | At $400 per month | At $650 per month |
|---|---|---|---|
| 1 | $3,000 per year | $4,800 per year | $7,800 per year |
| 3 | $9,000 per year | $14,400 per year | $23,400 per year |
| 5 | $15,000 per year | $24,000 per year | $39,000 per year |
| 10 | $30,000 per year | $48,000 per year | $78,000 per year |
Formula: providers × assumed monthly rate × 12. Setup, interfaces, equipment, internal time, taxes, and additional services are excluded.
A worked budget for a three-provider practice
Assume three providers at $400 each per month, $150 in monthly practice additions, $6,000 in one-time implementation payments, and $2,000 of internal transition labor value. All inputs are illustrative.
 Illustrative first-year budget. Internal labor value is separate from cash payments.
Recurring annual payments are $16,200. First-year cash spending is $22,200. Including internal transition labor value produces a first-year economic cost of $24,200. With unchanged rates, three-year cash spending is $54,600 and three-year economic cost is $56,600.
This example excludes taxes, new equipment, financing, usage overages, price increases, and future staffing changes. Add those items when they apply to your practice.
Step 4: Use the EHR Software Cost Estimator
Use the accompanying calculator to replace the sample assumptions with your own quotes. It calculates monthly operating payments, first-year cash spending, and three-year ownership cost. It is a budgeting tool, not a price quote.
| Calculator input | How to enter it |
|---|---|
| Licensed providers and monthly rate | Use the contracted rate; use an effective blended rate for a mixed provider group |
| Monthly practice fees and additions | Include required modules and estimated recurring usage |
| Implementation and equipment | Enter separate one-time cash payments |
| Transition payments | Include legacy overlap, extraction, or exit payments not already counted |
| Internal transition value | Enter staff hours × labor rate; exclude from cash totals |
| Yearly increase | Add an expected yearly increase to recurring charges in years two and three |
The calculation method
Monthly recurring payments = provider count × monthly provider rate + monthly additions.
First-year cash spending = monthly recurring payments × 12 + implementation + equipment + transition payments.
Three-year cash spending = annual recurring payments × [1 + (1 + increase) + (1 + increase)²] + one-time payments.
Three-year economic cost = three-year cash spending + internal transition value. The increase is an assumption, not a prediction. The model keeps provider count and usage unchanged and does not repeat implementation charges.
Renewals can change the decision
In the three-provider example, a 5% annual increase changes recurring payments from $16,200 in year one to $17,010 in year two and $17,860.50 in year three. Three-year cash spending becomes $57,070.50 after adding the $6,000 implementation payment. Including $2,000 in internal transition value produces $59,070.50.
Keep the estimate useful
Use written fees wherever possible. Record allowances and overages, avoid counting a bundled service twice, and keep internal time separate. For changing provider counts, staged launches, or irregular usage, build a year-by-year model instead of relying on a flat-rate calculation.
Step 5: Compare EHR Quotes on the Same Scope
A lower advertised subscription can produce a higher first-year bill. A longer evaluation period can change the result again. The following anonymous proposals use assumed prices and equivalent required workflows.
| Cost line | Quote A | Quote B |
|---|---|---|
| Monthly rate per provider | $300 | $450 |
| Annual subscriptions for 3 providers | $10,800 | $16,200 |
| Required additions per month | $400 | $100 |
| Annual required additions | $4,800 | $1,200 |
| One-time implementation | $8,000 | $3,000 |
| First-year cash spending | $23,600 | $20,400 |
| Three-year cash spending | $54,800 | $55,200 |
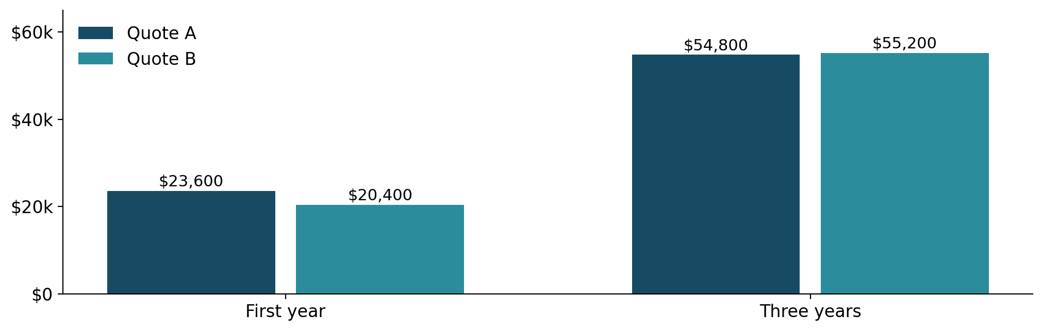 Illustrative cash comparison at unchanged rates. Quote B costs less in year one; Quote A costs $400 less over three years.
The comparison excludes internal labor, equipment, taxes, renewals, and unlisted usage. It does not establish which proposal delivers better service. Validate workflow fit, migration quality, support, and contract terms alongside the numbers.
Compare the operational scope
Use a shared checklist covering clinical documentation, scheduling, billing, patient engagement, specialty workflows, AI capabilities, interfaces, implementation, support, and exit terms. Ask vendors to fill missing fields. A blank amount should not be interpreted as free.
If revenue cycle management services are included, identify the responsibilities and fee basis separately. Billing software provides tools; an outsourced service also supplies labor. Compare both the payments and the work each proposal covers.
Specialty Workflows and AI Change Package Value
A useful cost comparison follows the services your practice delivers. Demonstrate the whole workflow before deciding whether a package can replace existing tools.
| Practice focus | Workflow to demonstrate | Cost question |
|---|---|---|
| Allergy and immunology | Testing, extracts, vial preparation, injection records, follow-up | Which specialty tools and inventory connections are included? |
| ENT with allergy | ENT encounter through allergy testing and ongoing treatment | What modules or interfaces connect these services? |
| Pulmonary care | Testing documentation, equipment results, follow-up, biologics | Does the proposed interface support your exact equipment? |
| Infusion and biologics | Inventory, authorization, administration, charge capture | Which tasks require separate software or services? |
Use the same approach when exploring allergy and immunology software, ENT and allergy workflows, or infusion and biologics software. Ask the team to demonstrate the services you actually deliver, then confirm their package and implementation costs.
For patient engagement tools, clarify whether messaging, reminders, intake, and related usage are included or separately billed. Budget the expected monthly volume and check the overage rules.
What does AI add to EHR pricing
Define the task first: drafting a note, finding chart information, or helping staff with administrative work. Ask whether the capability is included in the proposed package. Confirm provider or practice licensing, usage allowances, prerequisites, review steps, onboarding, and overage fees before assigning it a budget.
Test whether the result appears in the correct workflow and how clinicians or staff review it. Measure note completion, manual transfers, rework, and staff handling time during a pilot. A demonstration establishes behavior; it does not establish that a capability is included in the quoted package.
How to evaluate return on investment
Record a baseline before implementation. Financial benefits may include removed duplicate subscriptions, reduced paid overtime, or additional collected contribution from demonstrably increased capacity. Use the same evaluation period for benefits and costs.
ROI percentage = (measured financial benefits − project costs) ÷ project costs × 100.
For example, $30,000 in measured benefits against $24,000 in project costs produces 25% ROI. These are assumed figures. Do not value the same saved hours as both reduced payroll and extra appointment capacity. Track usability and clinician experience separately when they cannot be credibly converted into dollars.
Step 6: Choose a Package That Earns Its Place
The best EHR or EMR cost is the total investment required to support your practice well. A low subscription loses its appeal if staff must maintain duplicate tools or repeat work. A larger package also needs justification when its additional capabilities will go unused.
Review actual use before renewing
In its April 2026 coverage of unused EHR features and avoidable spending, Medical Economics highlights the risk of continuing to pay for tools a practice does not use. Review licensed accounts, optional modules, and overlapping subscriptions before the next renewal.
For each item, record its owner, purpose, monthly cost, actual use, and replacement dependencies. Remove a tool only after confirming that the remaining workflow works and the contract permits the change. Evaluate discounts alongside minimum commitments, renewal terms, support scope, and exit costs.
Plan for reliability and an orderly transition
HealthIT.gov’s guidance for selecting or upgrading health IT, updated in April 2026, includes implementation partnerships and contingency planning. Assign responsibility for downtime procedures, training, and transition work before launch. Include the associated staff time and any external charges in your plan.
Explore ModuleMD pricing and packages
ModuleMD offers Essential, Professional, Premium, and Elite packages, with pricing available by inquiry. Explore ModuleMD pricing and packages to discuss your clinical, administrative, and specialty requirements. Confirm the exact features, services, and fees in your written proposal.
Bring your provider mix, locations, existing systems, migration needs, and interface list. Ask for an itemized estimate covering recurring payments, one-time implementation, training, support, and renewal terms. A clear scope makes the quote easier to compare and the launch easier to budget.
Frequently Asked Questions About EHR and EMR Costs
How much does an EHR system cost per month in 2026?
Multiply the number of billable providers or users by the quoted monthly rate, then add practice fees, required modules, and expected usage charges. Check the billing unit carefully: one physician account and several staff accounts may not be priced the same way.
How much does EMR software cost for a small practice?
The cost depends on the plan, provider mix, required workflows, and services. For illustration, one provider at an assumed $400 monthly rate would pay $4,800 a year for that subscription alone. Implementation and any additional fees would increase the budget.
What is included in EHR implementation costs?
The contract may include configuration, migration, interfaces, training, and launch support. Add applicable equipment, legacy-system overlap, and staff participation. Ask for deliverables and responsibilities for every line item.
How much does EHR maintenance cost?
Start with the maintenance and support included in your agreement. Add separately charged upgrades, interface upkeep, IT support, equipment replacement, and ongoing training as applicable. There is no universal annual maintenance rate established by the current sources used in this guide.
What is the best EHR or EMR pricing plan?
Choose the lowest total-cost package that reliably supports your required workflows, implementation, and support needs. Compare the first year and later years, and test specialty tasks before deciding whether a higher tier is worth its additional fee.
How do I estimate the cost of switching EHR systems?
Add new implementation costs to any old-system extraction, termination, archive, and overlap charges. Include validation and training time separately from cash payments. Confirm what historical data will remain accessible after the switch.
Does free EHR software have operating costs?
A zero license fee does not establish zero ownership cost. Check hosting, migration, integrations, maintenance, support, and internal administration.
How do I get an EHR software cost estimate?
Prepare your provider mix, locations, workflows, migration scope, and interface list. Request an itemized written proposal, then use the calculator to estimate monthly, first-year, and three-year costs.
Is an EHR cost estimator the same as a patient cost estimator?
No. An EHR software estimator budgets a practice’s technology purchase. A patient cost estimator addresses expected patient responsibility for care. If patient estimation tools are part of your desired package, ask about their capability and fee separately.